
Retatrutide Research: What Scientists Are Learning About Triple-Receptor Agonism
Few investigational peptides have generated as much scientific interest in recent years as retatrutide.
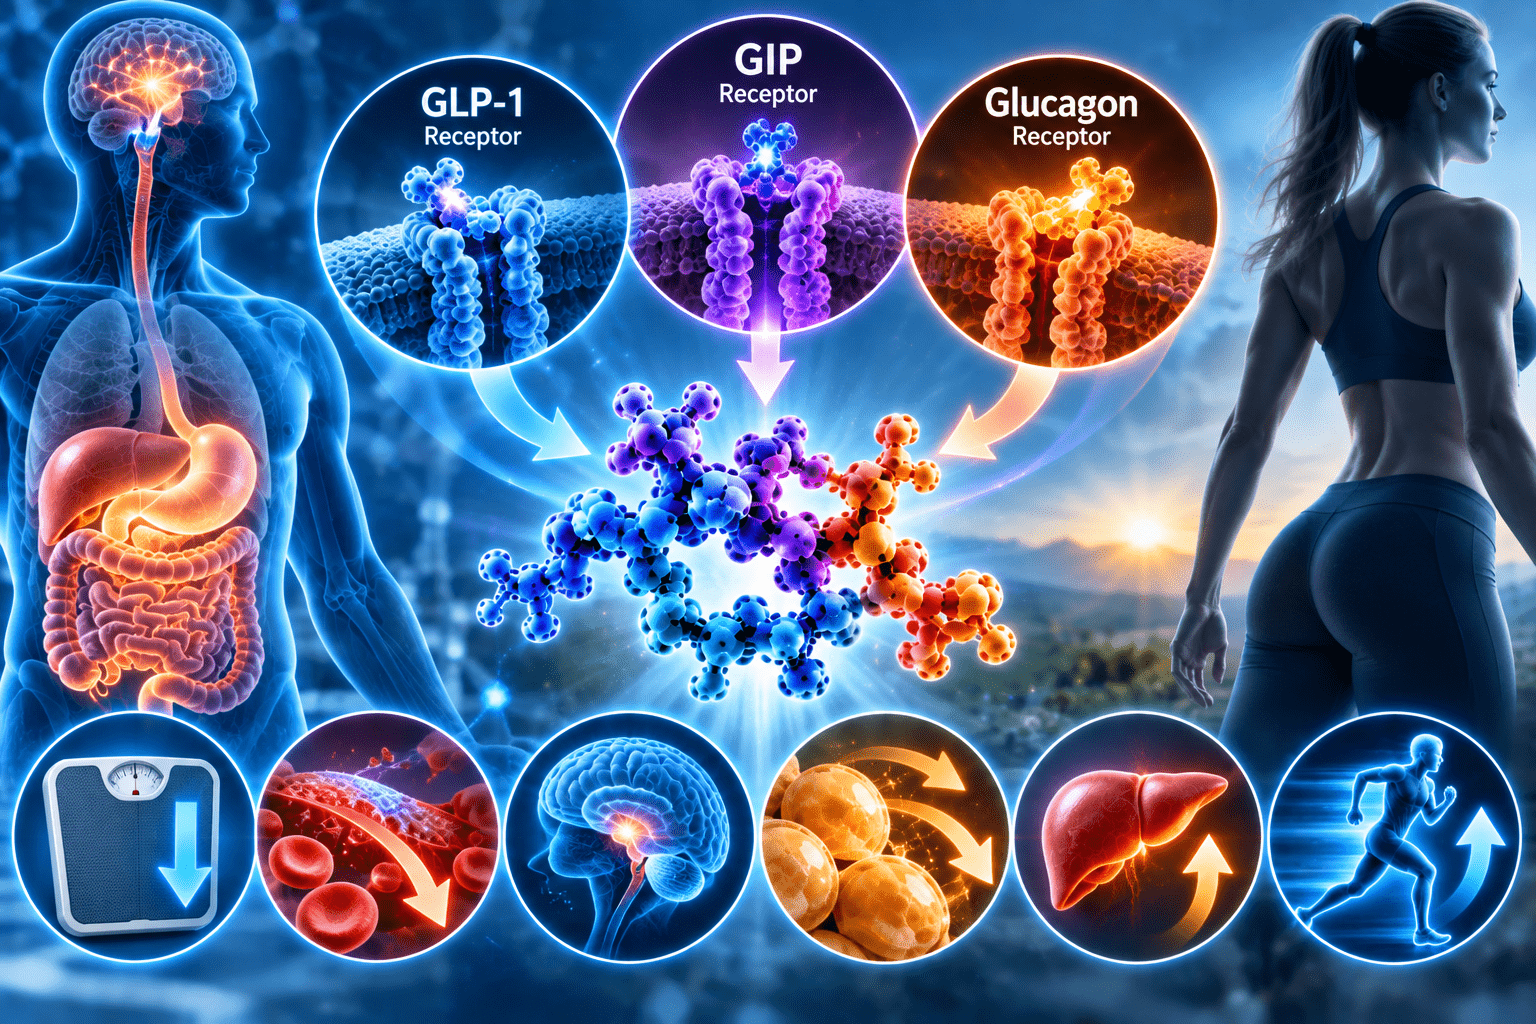
Retatrutide represents an important evolution in metabolic peptide research because it was engineered to activate not one, not two, but three hormone receptors involved in metabolism:
This makes retatrutide a triple hormone receptor agonist.
The idea behind this approach is fascinating. Rather than concentrating on a single metabolic pathway, researchers are investigating whether several complementary biological signals can be coordinated within one engineered peptide.
And in 2026, the retatrutide story became considerably more interesting.
From GLP-1 to Triple Agonism
To understand retatrutide, it helps to understand how metabolic peptide research reached this point.
GLP-1 receptor agonists demonstrated that targeting the glucagon-like peptide-1 pathway could produce significant effects on glucose regulation, appetite and body weight.
Researchers then investigated dual agonism.
Tirzepatide, for example, activates both GIP and GLP-1 receptors.
Retatrutide adds a third component:
glucagon receptor agonism.
That creates the combination:
GIP + GLP-1 + glucagon
The scientific question is whether these three signals can complement one another in ways that produce metabolic effects beyond those achievable through a single receptor.
Why GLP-1?
GLP-1 is an incretin hormone produced primarily in the intestine.
Its biological actions include glucose-dependent stimulation of insulin secretion, effects on glucagon secretion, slowing of gastric emptying and signaling related to appetite and food intake.
Those characteristics explain why GLP-1 became such an important metabolic research target.
But metabolism involves far more than one hormone.
Why GIP?
GIP—glucose-dependent insulinotropic polypeptide—is another incretin hormone.
Like GLP-1, GIP participates in nutrient-responsive insulin secretion.
The success of dual GIP/GLP-1 receptor agonism helped renew scientific interest in how these two incretin pathways interact.
Retatrutide preserves both components while adding another pathway.
Why Add Glucagon?
This is where the science becomes especially interesting.
Glucagon is commonly associated with increasing blood glucose because it signals the liver to make stored energy available.
So why deliberately activate its receptor in a metabolic drug?
Because glucagon has other physiological effects.
Glucagon signaling also participates in:
- energy expenditure
- lipid metabolism
- hepatic metabolism
- amino-acid metabolism
- mobilization of stored energy
Researchers hypothesized that glucagon receptor activation might contribute useful metabolic effects if its activity could be appropriately balanced by the GLP-1 and GIP components.
Retatrutide is essentially an experiment in achieving that balance within a single molecule.
What Did Early Human Research Find?
Retatrutide attracted enormous attention following its Phase 2 obesity trial.
The randomized trial included adults with obesity or overweight and investigated several retatrutide dose levels over 48 weeks.
At the highest studied maintenance dose, mean body-weight reduction reached approximately 24% at 48 weeks, while participants receiving placebo experienced only a small reduction.
Perhaps even more interestingly, average weight loss had not clearly plateaued at the end of the trial.
That raised an obvious question:
What would happen in a longer Phase 3 study?
By 2026, researchers had an answer.
The 2026 TRIUMPH-1 Results
In May 2026, Eli Lilly announced topline results from the Phase 3 TRIUMPH-1 obesity trial.
According to Lilly, participants receiving the 12 mg retatrutide regimen lost an average of 28.3% of their body weight after 80 weeks, corresponding to approximately 70.3 pounds on average.
Approximately 45.3% of participants achieved at least 30% body-weight reduction.
An extension involving participants who began with a BMI of at least 35 continued to 104 weeks. Lilly reported average weight reduction reaching approximately 30.3% in that group.
These were company-reported topline Phase 3 results, so detailed peer-reviewed publication and regulatory evaluation remain important parts of the evidence process.
Nevertheless, the findings significantly advanced the scientific story surrounding triple-receptor agonism.
Why the Results Matter Scientifically
The importance of retatrutide isn’t simply that a large amount of weight loss occurred.
The bigger question is why.
GLP-1 and GIP signaling can influence appetite, food intake and metabolic regulation.
Glucagon receptor activity may potentially add effects involving energy expenditure and substrate metabolism.
Researchers are therefore investigating whether triple agonism attacks metabolic dysfunction from several directions simultaneously.
In simplified terms, the strategy may involve influencing both:
energy coming in
and
energy being used.
Actual physiology is considerably more complicated, but this illustrates why the glucagon component has attracted so much attention.
Beyond Body Weight
Another major development is that retatrutide research has expanded beyond a number on the scale.
In June 2026, Lilly presented additional results involving obesity-related conditions.
The company reported improvements across areas including:
- type 2 diabetes
- knee osteoarthritis pain
- obstructive sleep apnea
- body weight
- A1C
For example, in TRANSCEND-T2D-1, Lilly reported A1C reductions of up to approximately 2 percentage points and body-weight reductions of up to 16.8% at 40 weeks.
These results matter because obesity is not an isolated condition.
It interacts with cardiovascular disease, sleep apnea, joint disease, liver disease, insulin resistance and numerous other health problems.
Modern metabolic peptide research therefore increasingly asks not merely:
“How much weight is lost?”
but:
“What happens to the diseases associated with metabolic dysfunction?”
What About Osteoarthritis?
The knee osteoarthritis findings are particularly interesting.
Excess body weight increases mechanical stress on weight-bearing joints.
Adipose tissue is also metabolically active and participates in inflammatory signaling.
Substantial weight reduction could therefore potentially influence osteoarthritis through several mechanisms.
Lilly reported substantial reductions in knee osteoarthritis pain in its Phase 3 program.
However, this does not automatically establish that retatrutide directly repairs cartilage or regenerates joints.
That distinction is essential.
An improvement in a clinical outcome can occur through indirect mechanisms without demonstrating tissue regeneration.
What About Sleep Apnea?
Obesity is a major risk factor for obstructive sleep apnea.
Fat deposition and anatomical changes around the upper airway can contribute to airway obstruction during sleep.
Substantial weight reduction can therefore improve sleep apnea in some individuals.
Lilly reported meaningful reductions in sleep-apnea severity in its retatrutide program.
Again, researchers will be interested in understanding how much of this effect is mediated by weight loss versus other metabolic changes.
What About Side Effects?
Powerful biological effects frequently come with tradeoffs.
As with other incretin-based therapies, gastrointestinal adverse events have been important in retatrutide trials.
Reported events have included:
- nausea
- diarrhea
- vomiting
- constipation
- decreased appetite
The frequency and severity can vary according to dose and escalation strategy.
This is one reason Phase 3 research is so important.
A drug isn’t evaluated solely according to its maximum efficacy.
Researchers and regulators must consider the overall balance of:
efficacy + safety + tolerability + durability
Retatrutide Is Still Investigational
This point is particularly important for an educational research-peptide article.
Strong clinical trial results do not automatically mean a compound is an approved medication.
As of this article’s September 2026 publication context, retatrutide remains investigational.
Lilly has indicated that regulatory submission is planned following completion and analysis of its development program.
Until regulatory review occurs, retatrutide should not be described as an FDA-approved treatment.
This distinction is especially important because products marketed online under the retatrutide name are not equivalent to an FDA-approved retatrutide medicine.
Why Researchers Are Watching Retatrutide
Retatrutide could ultimately be important for reasons extending beyond the compound itself.
It represents evidence supporting a broader concept:
Polyagonism
Instead of designing:
one molecule → one receptor
scientists can increasingly design:
one molecule → multiple coordinated receptors
That concept could potentially extend well beyond obesity.
Researchers may eventually develop multi-receptor molecules targeting other combinations involved in inflammation, neurological disease, endocrine signaling and metabolic disorders.
Could Four-Receptor Molecules Come Next?
Possibly.
But more receptors do not automatically mean better results.
The real challenge is balance.
Every receptor can produce multiple downstream effects.
Increasing activity at one receptor may improve one outcome while worsening another.
Future peptide engineering therefore isn’t simply about adding targets.
It is about finding the optimal combination and relative activity.
Scientists are effectively attempting to tune biological signaling.
The Bigger Lesson From Retatrutide
Retatrutide illustrates how dramatically peptide engineering has advanced.
Researchers started with naturally occurring hormones.
They learned how those hormones communicate with receptors.
They modified peptide structures to extend their duration.
They combined receptor activities.
And now they are attempting to coordinate three metabolic signaling systems within one molecule.
That progression represents something larger than the development of another obesity drug.
It demonstrates how modern peptide science is moving toward programmable biological signaling.
Retatrutide may eventually become an important therapeutic medicine, or future compounds may improve upon its design.
Either way, the research has already made one thing clear:
The future of metabolic peptides is unlikely to be limited to one receptor at a time.